Non-Surgical Esophageal Injury in Critically Ill Patients: Clinical Characteristics, Complications, and Interdisciplinary Management
DOI:
https://doi.org/10.14740/gr2180Keywords:
Esophageal injury, Esophageal perforation, Critical care, Mediastinitis, Endoscopy, Interdisciplinary managementAbstract
Background: Non-surgical esophageal injury can cause mediastinal or pleural infection, organ dysfunction, and prolonged critical care. Evidence in critically ill patients regarding perforation status, diagnostic pathways, and treatment remains limited. We described clinical characteristics, complications, management, and outcomes and compared patients with and without confirmed perforation.
Methods: We retrospectively analyzed 42 adults with non-surgical esophageal injury treated for more than 24 h in a surgical intensive care unit between 2017 and 2023. Patients were compared by confirmed perforation. Categorical variables were analyzed using chi-square or Fisher’s exact tests, continuous variables using the Mann–Whitney U test, and exploratory associations using Spearman’s rank correlation.
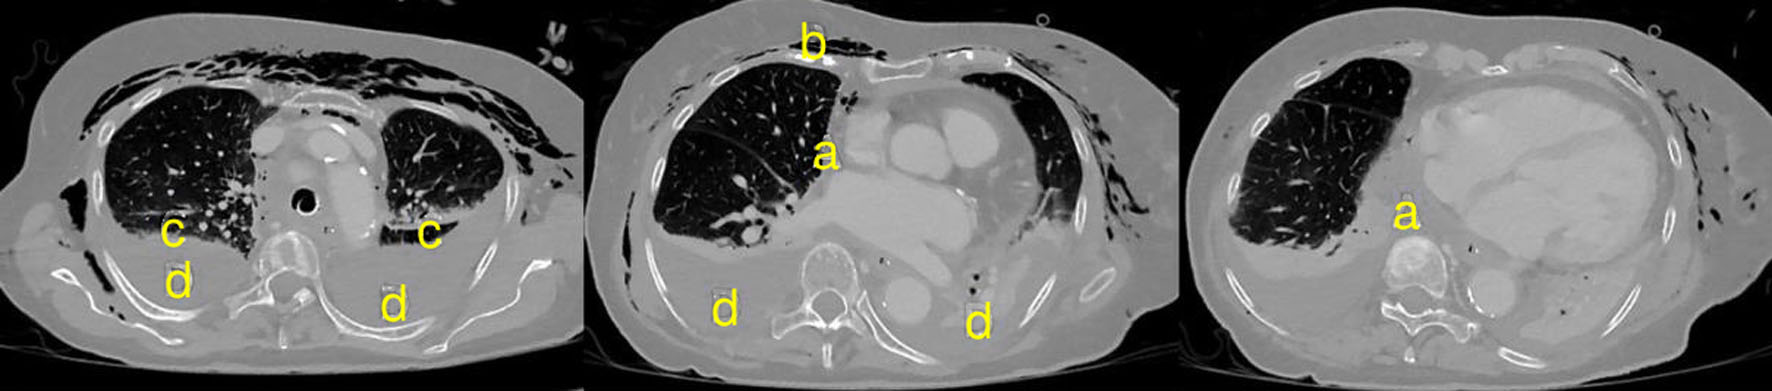
Results: Mechanical trauma was most common (83.3%); 22 patients (52.4%) had perforation. Endoscopy was performed in 97.6% and computed tomography in 78.6%. Compared with patients without perforation, those with perforation had more sepsis (45.5% vs. 0.0%), septic shock (31.8% vs. 0.0%), acute kidney injury (27.3% vs. 0.0%), mediastinitis (50.0% vs. 5.0%), and pleural empyema (36.4% vs. 0.0%). Intensive care unit stay was longer with perforation (12.0 (5.8–22.3) vs. 4.5 (2.8–8.0) days; P = 0.005). Intracavitary endoscopic vacuum therapy was used in 19 patients, including two who also received a stent; surgery in 15; and both treatments in eight. Sixteen received supportive care without defect-directed intervention. Endoscopic vacuum therapy started within 12 h of intensive care unit admission in 18/19 patients and within 16 h in all. In-hospital mortality was 2.4% (n = 1).
Conclusions: Non-surgical esophageal injury is heterogeneous. Confirmed perforation was associated with greater morbidity and longer intensive care treatment. Early computed tomography and endoscopy, repeated interdisciplinary reassessment, and individualized supportive, endoscopic, or surgical therapy are central to management.
Published
Issue
Section
License
Copyright (c) 2026 The authors

This work is licensed under a Creative Commons Attribution 4.0 International License.